- Your cart is empty
- Continue Shopping


Manual vs Digital BP Apparatus: Which Is More Accurate?

Quick Answer
In trained hands, a calibrated manual (aneroid or mercury) BP apparatus with a stethoscope is the more accurate instrument, and it remains the reference doctors compare everything else against. In an ordinary home, a clinically validated upper-arm digital monitor is the more accurate choice, because the manual method depends on hearing, timing and technique that most people never learn, and a small error in any of them is larger than the device’s own error. The honest answer is therefore: manual for clinics and trained users, digital for home, and for both, the cuff size, the arm position and five minutes of rest matter more than the price tag.
Ask ten people in Pakistan which is more accurate, the doctor’s dial-and-pump apparatus or the electronic machine at home, and nine will say the doctor’s. They are half right. The manual apparatus, whether the mercury column of the older clinics or the aneroid dial that has replaced it, measures pressure directly and, when it is calibrated and the person using it knows how to listen, it is as close to the truth as a non-invasive reading gets. Comparison studies from India and Bangladesh in settings much like ours have repeatedly found that a calibrated aneroid agrees more closely with the mercury standard than a digital monitor does, sometimes by a margin of 3 mmHg or more on the diastolic number.
The catch is the phrase “when the person using it knows how to listen.” The manual method requires you to inflate the cuff, release air at about 2 to 3 mmHg per second, hear the first tapping sound and the moment it disappears through a stethoscope, and read a moving needle at both instants. Every one of those steps is a place to be wrong by 5 to 10 mmHg, and a relative at home, or a rushed assistant in a busy clinic, is often wrong at more than one of them. A digital monitor removes all of that and replaces it with a sensor and an algorithm that are consistent every time, which is why hypertension guidelines worldwide now recommend validated automatic monitors for home use. This guide sets out what each type does well, where each goes wrong, what the accuracy studies actually show, and how to choose between a manual sphygmomanometer and a digital blood pressure monitor for your situation.
How Each Type Measures Blood Pressure
| Feature | Manual (aneroid / mercury) | Digital (automatic) |
| Method | Auscultatory: you listen for Korotkoff sounds with a stethoscope while reading the gauge | Oscillometric: a sensor detects pulse vibrations in the cuff and an algorithm calculates systolic and diastolic |
| What is measured directly | Pressure, on a dial or column | Mean arterial pressure; the two numbers are estimated from it |
| Operator skill needed | High: hearing, deflation rate, needle reading | Low: wrap cuff, press start |
| Reading in noisy room | Difficult | Unaffected |
| Irregular heartbeat (atrial fibrillation) | Experienced user can still read it | Many monitors misread or refuse; better models flag it |
| Very stiff arteries, elderly | Reads correctly if sounds are audible | Can overestimate or underestimate |
| Power | None | Batteries or adapter |
| Calibration | Needs checking every 6 to 12 months; aneroid drifts with knocks | Needs checking every 1 to 2 years; validated models drift less |
| Typical stated accuracy | ±3 mmHg on the gauge | ±3 mmHg on pressure, ±5% on pulse |
| Price in Pakistan | Rs 2,500 to 12,000 | Rs 3,500 to 15,000 |
The critical difference is in the second row. A manual apparatus measures pressure and you decide the numbers by ear. A digital monitor measures the pattern of vibrations in the cuff as it deflates, finds the point of maximum oscillation, which corresponds to mean pressure, and then applies a manufacturer’s formula to estimate systolic and diastolic from the shape of the curve. That formula is tuned on healthy adults with regular rhythms. In an elderly person with stiff arteries, a patient in atrial fibrillation, a pregnant woman, or someone with a very large or very thin arm, the curve looks different and the estimate can be off, which is exactly why doctors still keep a manual set in the room.
What the Accuracy Studies Show
| Finding | Detail | What it means for you |
| Aneroid closer to mercury than digital | In community studies from South Asia, calibrated aneroids agreed with the mercury standard within about 1 mmHg on diastolic; digital monitors differed by 3 to 4 mmHg | Manual wins on device accuracy when used correctly |
| Digital monitors moderate at detecting hypertension | Pooled analyses find digital devices identify roughly 65 to 80% of true hypertension found by mercury | Digital can miss some hypertension; trend over weeks, not one reading |
| Operator error in manual method is large | Rounding to the nearest 10, deflating too fast, wrong cuff size and hearing errors each add 5 to 10 mmHg | In untrained hands, manual loses its accuracy advantage completely |
| Aneroid gauges drift | Surveys of clinics find a meaningful share of aneroids more than 4 mmHg off calibration | A manual gauge is only accurate if someone checks it |
| Wrist digital monitors least reliable | Consistently the least reliable type in comparisons | Buy upper-arm, not wrist |
| Validated digital models perform well | Monitors that pass independent protocols read within acceptable limits for most adults | Look for validation, not price |
Read together, the studies say something more useful than “manual is better.” They say that the manual apparatus has a higher ceiling and a lower floor: in expert, calibrated hands it is the most accurate; in careless hands or with a dropped, uncalibrated gauge it can be the least. The digital monitor has a narrower band: rarely as precise as the best manual reading, rarely as wrong as the worst one. For a family in Lahore checking an elderly parent’s pressure every morning, the narrower band is the safer bet, because the person taking the reading changes from day to day and nobody is deflating the cuff at exactly 2 mmHg per second.
Where the Manual Method Goes Wrong at Home
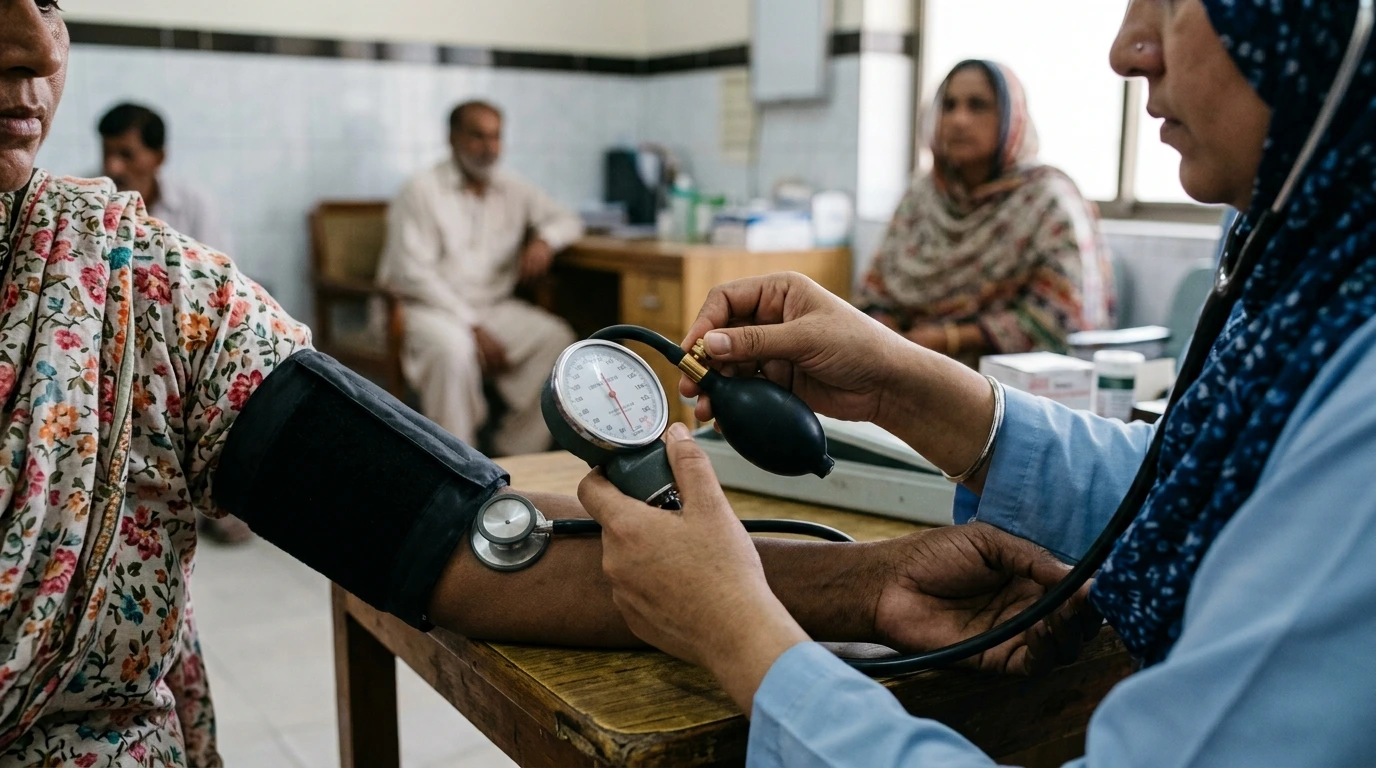
The first error is the cuff. A standard adult cuff fits an upper arm of roughly 22 to 32 cm around; on a heavier arm it reads high, on a thin arm it reads low, and the same is true for digital cuffs. The second is deflation speed. Letting the air out fast to finish sooner makes the needle sweep past the true systolic point before you register the first sound, so you read low, and the same rush blurs the diastolic. The third is hearing. Korotkoff sounds are soft, a room with a fan or television masks them, and a cheap stethoscope makes the problem worse; the stethoscope matters as much as the gauge. The fourth is rounding: almost everyone reads a moving needle to the nearest 10, which is why so many manual readings end in zero. The fifth is calibration. An aneroid gauge that has been dropped, or has simply aged, can sit several mmHg off and there is no way to know without comparing it against a reference. We described the full technique, including palpation when no stethoscope is available, in our guide to manual BP monitoring. None of these errors is a reason to avoid a manual set; they are reasons to learn it properly or to leave it to someone who has.
Where the Digital Monitor Goes Wrong at Home
Digital monitors fail differently. They are almost never wrong because of the operator’s ears; they are wrong because of movement, talking, a full bladder, crossed legs, an unsupported arm, a cuff placed over a sleeve, or a reading taken immediately after climbing stairs, all of which shift the result by 5 to 15 mmHg and none of which the machine can detect. They are also wrong for a specific group of people. Irregular rhythms confuse the oscillometric algorithm, which is why a monitor that displays an irregular-heartbeat symbol is worth paying for, a point we made in our guide to what the two blood pressure numbers mean. Wrist monitors add positioning error on top and are the least reliable type. And a cheap unvalidated monitor can simply be badly tuned; the price difference between a validated brand and an unbranded import is often the difference between a monitor that agrees with the clinic and one that does not. Check any new digital monitor against a clinic reading once, and repeat the comparison yearly.
Which Should You Buy?
| Situation | Better choice | Why |
| Family monitoring at home, no medical training | Validated upper-arm digital | Consistent regardless of who takes the reading; keeps a log |
| Elderly patient with irregular pulse | Digital with irregular heartbeat detection, plus occasional manual check | Flags rhythm problems; manual confirms the number |
| Nurse, doctor, medical student, home nurse | Manual aneroid plus stethoscope | Reference accuracy, no batteries, teaches the skill |
| Clinic or ward | Wall or desk mounted aneroid for reference, digital for triage | Durable, always in place, cannot be dropped; the digital saves time |
| Pregnancy monitoring | Manual by a trained person, or a digital validated for pregnancy | Algorithms are less reliable in pregnancy |
| Load-shedding areas, emergencies | Manual aneroid | Works with no power; the digital may be flat when needed |
| Very large or very small arm | Either, with the correct cuff size | Cuff size is the bigger error either way |
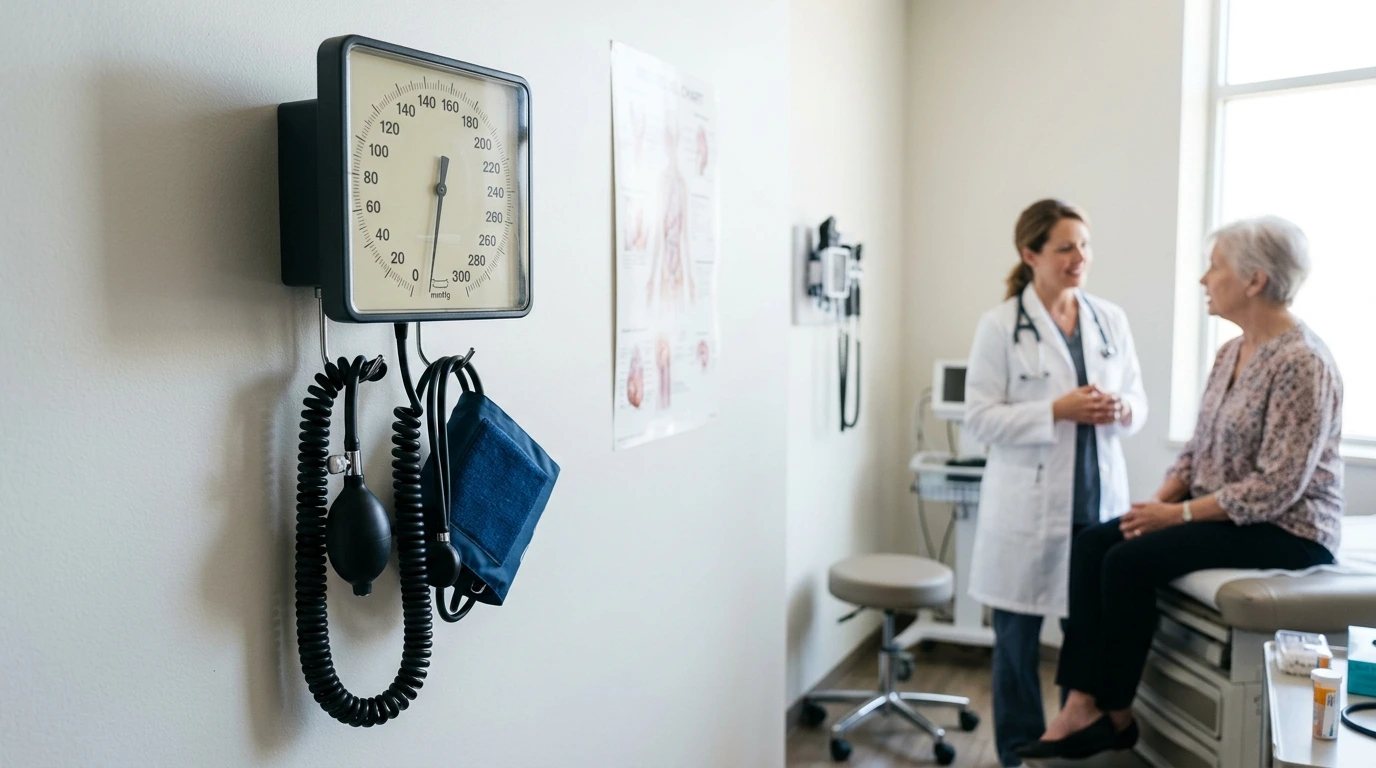
For a clinic, the reference instrument does not have to be portable, and the most reliable way to keep an aneroid gauge accurate is to keep it from being dropped. A wall-type aneroid sphygmomanometer with a large dial mounted at eye level solves the reading and calibration problems at once: the needle is easy to read without rounding, the gauge never travels in a bag, and one calibration check a year is usually enough. Mercury columns, still found in older Pakistani clinics, remain accurate but are being phased out worldwide because of mercury toxicity, and a good aneroid is the accepted replacement. For the home, the practical advice is simpler: buy a validated upper-arm digital monitor with the right cuff size, learn the correct posture, take two readings a minute apart each morning, and compare the monitor against the clinic reading once a year. Both types agree on one thing, which our normal blood pressure by age chart makes clear: a single reading, from any device, means very little, and the pattern over weeks means everything.
Frequently Asked Questions
Which is more accurate, manual or digital BP apparatus?
A calibrated manual aneroid or mercury apparatus used by a trained person is the more accurate instrument and is the reference standard. For most homes, a validated upper-arm digital monitor gives more accurate results in practice, because it removes the hearing and technique errors that make untrained manual readings unreliable.
Why does my digital BP machine read different from the doctor’s?
Common causes are talking or moving during the reading, an unsupported arm, a cuff over clothing, a wrong cuff size, a reading taken soon after activity, or an unvalidated cheap monitor. Also, pressure is often higher at the clinic from anxiety. Compare the two on the same arm, a minute apart, after five minutes of rest.
Is an aneroid sphygmomanometer as accurate as mercury?
Yes when calibrated, within about 1 to 3 mmHg. Aneroid gauges drift if dropped or aged, so they need checking against a reference every 6 to 12 months. Wall or desk mounted aneroids drift less because they are not carried and knocked about.
Are wrist blood pressure monitors accurate?
They are the least reliable type in comparison studies because the reading depends heavily on holding the wrist exactly at heart level and still. An upper-arm digital monitor is the better home choice; wrist monitors suit only people whose arms cannot take a cuff.
How often should a BP apparatus be calibrated? Aneroid gauges every 6 to 12 months, or immediately after being dropped; digital monitors every 1 to 2 years, or whenever readings start disagreeing with the clinic. A practical home check is to compare your monitor against the clinic’s device on the same arm during a routine visit.
