- Your cart is empty
- Continue Shopping


How Does a Fetal Doppler Work, When Can You Hear the Heartbeat, and Is It Safe at Home?

Quick Answer
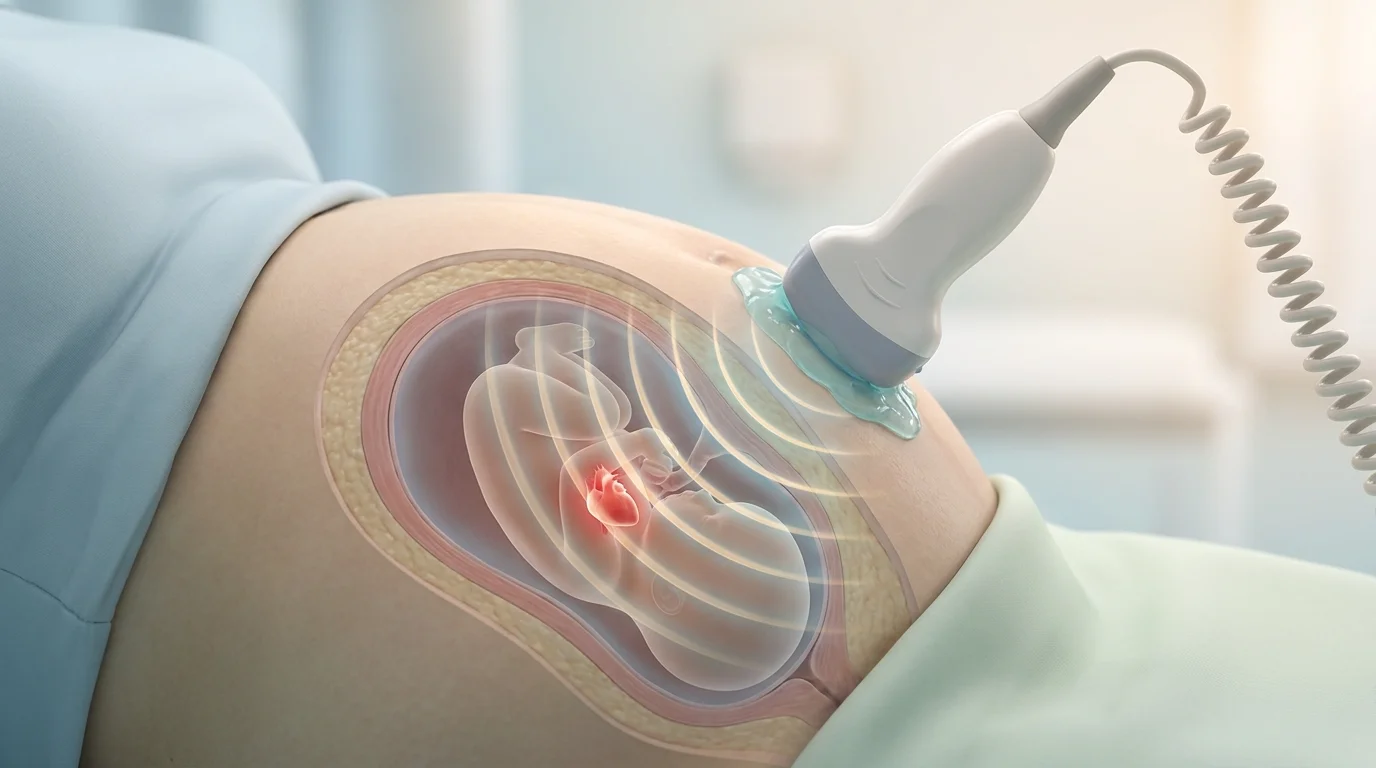
A fetal doppler is a small handheld ultrasound device. Its probe sends continuous sound waves at 2 or 3 MHz into the abdomen; when those waves bounce off the baby’s moving heart walls and blood, they return at a slightly changed frequency, and the device turns that change into the galloping sound you hear and a number on the screen. In a clinic, a doppler usually finds the heartbeat from about 10 to 12 weeks, sometimes 8 to 10 weeks with a 3 MHz probe on a slim mother; at home, with less experience, expect it to be reliable only from 12 to 16 weeks, and most devices are labelled for use after week 12. A normal fetal heart rate is about 110 to 160 beats per minute, roughly twice the mother’s pulse, which is the main way to tell the two apart. Short, occasional use has shown no evidence of harm, but the FDA classes these devices as prescription-only and advises against unsupervised home use, and UK and Australian maternity bodies warn that a heartbeat heard at home can give false reassurance: if your baby’s movements have reduced after 24 weeks, contact your doctor or hospital immediately, whatever the doppler says. The doppler is a listening tool, not a wellbeing test.
The sound of a baby’s heartbeat is the moment most parents in Pakistan remember from their first ultrasound, and the pocket fetal doppler puts that sound within reach at home for the price of a good blood pressure monitor. Clinics, midwives and lady health workers use the same device at every antenatal visit, which is why families assume it is a safety instrument, something to confirm that all is well on a day when the baby feels quiet. That assumption is where the trouble lies, and this guide is written to give an honest account of both sides: what the device actually does and does well, when it works and why it sometimes cannot find anything, and the specific situation, reduced movements, in which it should never be the thing you rely on.
The guide covers the physics in plain terms, the difference between a doppler, a fetoscope and a CTG machine, the week-by-week timeline for hearing the heartbeat and the reasons it is delayed in some pregnancies, how to recognise the baby’s heartbeat and not the mother’s pulse or the placenta, the correct way to use the probe, the actual safety evidence and official positions, and the prices of the fetal dopplers on our store. If you are a clinic or a midwife choosing a unit, our fetal doppler and sonicaid range lists the pocket and desktop models we stock.
How the Device Works
Ultrasound is sound at a frequency far above hearing. A fetal doppler uses continuous-wave ultrasound: one crystal in the probe transmits all the time and a second one listens all the time. When sound reflects off something that is moving towards or away from the probe, its frequency shifts slightly, exactly as the pitch of a passing motorbike rises as it approaches and falls as it leaves. The baby’s heart walls and the blood rushing through the heart and umbilical cord are moving fast, so the reflected sound returns shifted, and the circuitry subtracts the original frequency to leave only the shift, which happens to fall within the range of human hearing. That difference signal is what comes out of the speaker as the familiar whooshing gallop, and the device counts the beats to display a heart rate.
Two details matter in practice. First, sound at these frequencies does not travel through air, so a layer of ultrasound gel between the probe and the skin is not optional; without it most of the signal reflects straight back off the skin surface. Second, the probe frequency decides what the device can reach. A 3 MHz probe gives finer detail at shallow depth and is better in early pregnancy and on slim mothers; a 2 MHz probe penetrates deeper, to 10 cm or more, and is better in later pregnancy and for mothers with a higher body weight. Many pocket dopplers come with one fixed probe, so a 3 MHz unit that found the heartbeat easily at 14 weeks may struggle at 36 weeks on the same mother, and a 2 MHz unit may find nothing at 11 weeks.
| Device | How it works | When it detects the heartbeat | What it tells you | Who uses it |
| Fetoscope or Pinard horn (Rs 500 on our store) | A trumpet-shaped stethoscope pressed to the abdomen; no electronics | Usually from about 18 to 20 weeks, later in heavier mothers | That a heartbeat is present and its approximate rate, heard by one listener | Midwives, lady health workers, traditional dais |
| Pocket fetal doppler (Rs 6,500 to 30,000) | Continuous-wave ultrasound at 2 or 3 MHz; amplifies the Doppler shift as sound and displays a rate | From about 10 to 12 weeks in experienced hands; reliably 12 to 16 weeks at home | Presence and rate of the heartbeat at that moment; both parents can hear it | Clinics, midwives, home users |
| Desktop fetal doppler with display (Rs 70,000 on our store) | Same principle, larger speaker, rechargeable, often with waveform display | As above | As above, with clearer sound for teaching and clinic use | Clinics and labour rooms |
| CTG machine (cardiotocograph) | Two transducers strapped to the abdomen record the fetal heart rate pattern and contractions continuously for 20 to 40 minutes | From about 26 to 28 weeks | The pattern of the heartbeat over time, accelerations, decelerations and variability, which is what actually tests fetal wellbeing | Hospitals; the test ordered for reduced movements after 26 weeks |
| Ultrasound scan | Pulsed ultrasound that produces an image | Cardiac activity visible from about 6 weeks on a transvaginal scan | Heart activity, size, growth, fluid, placenta position, anatomy | Sonographers and doctors |
The last two rows are the point. A pocket doppler tells you the baby’s heart is beating at this moment and how fast. It cannot tell you whether the baby is well, because wellbeing is judged from the pattern of the heart rate over time against movements and contractions, which is the CTG’s job, and from growth, fluid and blood flow, which is the scan’s. A baby can have a normal heart rate on a doppler and still be in difficulty.
When You Can Hear the Heartbeat
| Weeks of pregnancy | What to expect with a handheld doppler |
| Before 8 weeks | Not detectable with a handheld doppler; cardiac activity is seen on transvaginal ultrasound from about 6 weeks |
| 8 to 10 weeks | Occasionally found in a clinic with a 3 MHz probe on a slim mother with the probe low, just above the pubic bone; not something to expect at home |
| 10 to 12 weeks | Commonly found in a clinic; many home users still cannot find it; most devices are labelled for use from week 12 |
| 12 to 16 weeks | Usually found at home with patience; the uterus has risen above the pubic bone, so the probe position moves upward |
| 16 to 24 weeks | Easy to find for most people; the baby moves often, so the sound comes and goes |
| 24 weeks onward | Easy to find; the heart rate pattern, not the presence of a heartbeat, is what matters, and reduced movements need a CTG, not a doppler |
If you cannot find it, the usual reasons are these. The pregnancy is earlier than the dates suggest. The placenta is at the front of the uterus, between the probe and the baby, and its loud whooshing drowns the heartbeat. The mother’s body weight puts more tissue between probe and baby, which is where a 2 MHz probe helps. The uterus is tilted backward in early pregnancy. The bladder is empty, so the uterus sits lower and further back than expected before 12 weeks, or very full later on. Or, most often, the probe is too high: before 14 weeks the uterus is still a small organ just above the pubic bone and in the midline, not where the mother imagines her “tummy” to be. None of these means anything is wrong, and the only correct response to not finding a heartbeat at home is to stop after a few minutes and arrange a clinic check, not to keep searching for half an hour.
Baby’s Heartbeat or Your Own: Telling the Sounds Apart
| Sound | Rate | Character | What it is |
| Fast gallop, like a horse running or a train | 110 to 160 beats per minute | Clear double beat, fast, steady, changes rate slightly with movement | The baby’s heart |
| Slow regular thump | 60 to 100 beats per minute, the same as the pulse at your wrist | Single beat, slower; matches your own pulse exactly | Your own heartbeat through the aorta or a large vessel; the commonest false reassurance |
| Soft continuous whooshing wind, pulsing at the mother’s rate | Mother’s rate | Blowing, not beating | Blood flow through the placenta (placental souffle) |
| Whooshing that pulses at the baby’s rate | Baby’s rate | Blowing, in time with the fast gallop | Blood through the umbilical cord; counts as the baby |
| Sudden thuds, rumbles, static | Irregular | Loud and brief | The baby kicking, the mother’s bowel, the probe moving on the skin |
The single most useful check is to feel your own pulse at the wrist while listening. If the beat in the speaker matches the beat under your fingers, you are hearing yourself. Pakistani mothers are often told to “double it” when a slow sound is heard, on the idea that the placenta can be heard at twice the rate; the reliable approach is simpler: the baby’s heart is about twice as fast as yours and sounds like galloping, not thumping, and anything near your own rate is not the baby. Pocket dopplers display a rate but can lock on to the mother’s pulse and show 70 or 80 with confidence, so the number alone is not proof.
How to Use a Fetal Doppler Correctly
Lie back with the head and shoulders slightly raised and the knees bent, so the abdominal muscles are relaxed. Apply a generous blob of ultrasound gel, about the size of a Rs 10 coin, either to the skin or to the probe face; KY jelly or aloe gel will work in a pinch, but oils and lotions will not, and a 60 g tube of proper gel lasts more than fifty sessions. Before 14 weeks, start in the midline just above the pubic bone with the probe tilted slightly downward toward the pelvis; after 14 weeks, start a hand’s width below the navel and work outward. Move the probe slowly, a centimetre at a time, and tilt it rather than sliding it, because the heart is small and the beam is narrow. Pause for two or three seconds in each position; the sound appears abruptly when the beam crosses the heart. Once found, hold still, count or read the rate, listen for a minute, and stop. A session should take a few minutes at most, not because a few minutes more is proven to harm, but because no one has studied long and frequent home sessions, and the principle in medical ultrasound is to keep exposure as low as reasonably achievable. Wipe the probe clean with a soft cloth; do not immerse it or use alcohol on the probe face unless the manual permits it.
Is a Home Fetal Doppler Safe?
There are two separate safety questions, and the answers are different.
The first is the ultrasound itself. Pocket dopplers emit low-intensity continuous-wave ultrasound, typically under 10 mW per square centimetre, which is a fraction of what a diagnostic scanner uses, and decades of clinical use have produced no evidence of harm from brief listening. The FDA’s position, in its consumer update on fetal heartbeat monitors, is that although there is a lack of evidence of any harm, prudent use by trained providers is important, and that the concern with home use is uncontrolled exposure: there is no limit on how long one session lasts or how many sessions happen in a week. The FDA classes these devices as prescription devices for use by or under the supervision of a healthcare professional, not for over-the-counter sale, and its Office of Women’s Health has warned that untrained use could expose the fetus to prolonged and unsafe energy levels or produce information that is interpreted incorrectly. That is the honest position: brief use is very unlikely to cause harm; nobody has shown that daily twenty-minute searches are safe, and the FDA has not approved these devices for home use at all.

The second question is the more important one, and it has nothing to do with ultrasound energy. It is false reassurance. In around half of stillbirths, the mother had noticed that the baby’s movements had reduced beforehand, which is why reduced fetal movement is one of the elements of the NHS “Saving Babies’ Lives” programme and why midwives repeat the same message at every visit after 24 weeks: if movements reduce, call the same day. A home doppler undermines that message. A mother who feels fewer kicks, finds a heartbeat, and goes to bed reassured has been reassured by the wrong test. The BMJ reported in 2009 on women with reduced movements who were falsely reassured by a home doppler and delayed seeking care. The NHS advice to professionals, written by the charity Tommy’s, is blunt: do not use a home doppler or anything else to check at home; even if you hear a heartbeat, your baby may still be unwell and need to be checked in hospital. The Stillbirth Centre of Research Excellence in Australia states that there is no evidence that home dopplers reduce the risk of stillbirth and that they may cause life-threatening delay. After a petition by the charity Kicks Count passed 12,000 signatures, the UK retailer Mothercare stopped selling them.
| Situation | Is a home doppler the right tool? | What to do instead |
| Hearing the heartbeat together as a family between visits, after 12 to 16 weeks, for a few minutes | Acceptable, with realistic expectations and a short session | Nothing more needed |
| Could not find the heartbeat at home before 16 weeks | Not a sign of a problem by itself | Stop after a few minutes; ask the clinic to check at the next visit, sooner if you are worried |
| Reduced or changed movements after 24 weeks | No, under any circumstances | Call your doctor or the labour room the same day; a CTG and, if needed, a scan are the tests |
| Bleeding, pain, fluid leaking, fever, severe headache or swelling | No | Go to the hospital; the heartbeat does not change what you must do |
| Anxiety after a previous loss | Understandable, but the doppler tends to feed the anxiety rather than settle it | Talk to your obstetrician about more frequent checks or scans |
| Clinic, midwife, lady health worker use at antenatal visits | Yes; this is what the device is for | Pair with fundal height, movement history and blood pressure |
Fetal Doppler Prices in Pakistan
On our own store at the time of writing, a basic pocket fetal doppler is Rs 6,500, the Yuwell pocket doppler Rs 9,000, the Contec 10A pocket doppler Rs 10,000, the Neeva baby doppler Rs 18,000, and the Korean Bistos Hibebe units Rs 20,000 and Rs 30,000, with the Bistos BT-250 desktop fetal doppler for clinics at Rs 70,000 and a simple fetoscope at Rs 500. The price difference buys a clearer speaker, a rechargeable battery, a sturdier probe, a display that shows the rate steadily rather than jumping, and, on the Korean units, interchangeable 2 and 3 MHz probes. A clinic doing twenty checks a day should buy at the upper end; a family that wants to listen occasionally and understands the limits above is well served at the lower end, and would do better to spend the difference on a proper digital blood pressure monitor, because high blood pressure in pregnancy is a danger a home device genuinely can catch.
Fetal Dopplers We Stock
From a Rs 500 fetoscope to the Korean Bistos units with interchangeable 2 and 3 MHz probes. Every doppler ships with ultrasound gel; use it for a few minutes at a time, and remember that reduced movements after 24 weeks need a same-day call to your doctor, whatever the doppler says. Clinics and labour rooms can also see the Bistos BT-250 desktop fetal doppler (Rs 70,000).



Clinic grade, interchangeable probes
Bistos BT-220C Hibebe S Fetal Doppler (Korea)
₨ 30,000
Add to cart
Frequently Asked Questions
How does a fetal doppler work?
It sends continuous ultrasound waves at 2 or 3 MHz through gel into the abdomen. Sound bouncing off the baby’s moving heart and blood returns at a shifted frequency, and the device converts that shift into the galloping sound you hear and a heart rate on the screen. Gel is essential because ultrasound does not pass through air.
When can you hear the baby’s heartbeat with a fetal doppler?
In a clinic, usually from 10 to 12 weeks, occasionally 8 to 10 weeks with a 3 MHz probe. At home, expect it reliably from 12 to 16 weeks, and most devices are labelled for use from week 12. An anterior placenta, higher body weight, a tilted uterus or the probe held too high can all delay it, and not finding it early is not by itself a sign of a problem.
What is a normal fetal heart rate on a doppler?
About 110 to 160 beats per minute, which is roughly twice the mother’s resting pulse. A steady beat of 60 to 100 that matches your own pulse at the wrist is your heartbeat, not the baby’s. The rate varies minute to minute with the baby’s movement, which is normal.
Is it safe to use a fetal doppler at home every day?
Brief occasional listening has shown no evidence of harm, but the FDA classes fetal dopplers as prescription devices for use under professional supervision and has not approved them for home use, and nobody has studied long daily sessions. Keep any session to a few minutes. The bigger risk is false reassurance: a heartbeat heard at home does not mean the baby is well.
My baby is moving less but I can hear the heartbeat. Is that okay? No. Reduced movements after 24 weeks need a same-day call to your doctor or hospital for a CTG, whatever the doppler says. Around half of stillbirths are preceded by reduced movements, and a heartbeat on a pocket doppler cannot test the baby’s wellbeing. Do not wait until morning and do not keep checking with the doppler.
